
WEG Product Support
Warmer SW-C72L / Drape SD-CIR44
Slush SS-C90L / Warmer SW-R38L / Drape SD-DISC66
WEG Slush Machine Set Up
Warmer SW-R38L / Drape SD-REC44
Warmer SW-R58L / Drape SD-REC60
WEG Warmer Demonstration
Hypothermia Is Common. The Risks Are Not.
Up to 70% of surgical patients develop hypothermia perioperatively. Inadvertent hypothermia can be caused by cold operating rooms, effects from anesthesia , exposure to the environment and administration of cold intravenous or irrigation fluids. The adverse effects of unplanned hypothermia include increased blood loss, morbid cardiac events, impaired wound healing and increased mortality.1 Hypothermia is defined as a core body temperature below 36°C. If not deliberately induced, it is said to be inadvertent because it develops accidentally during a period when normal protective reflexes, such as shivering, are absent.4,5 Inadvertent hypothermia is preventable, and by increasing nurses’ knowledge and awareness, its incidence may be reduced.6 Preventing unplanned hypothermia increases patient comfort and prevents associated complications. It can be achieved by simple preventative measures.2 It is therefore essential that nurses, whether on surgical wards or operating room staff, have knowledge of the contributing factors, complications and methods of preventing inadvertent hypothermia. This combined with vigilant patient care will help to prevent or dramatically reduce the incidences of this condition.7
The Cost of a Complication Is Never Just Clinical
Surgical site infections are among the most expensive complications in perioperative care, and their rate is rising. A single postoperative infection can add approximately $51,364 in treatment costs for a trauma patient, part of a national burden estimated at $96 billion to $147 billion each year.8
Frequently Asked Questions
-
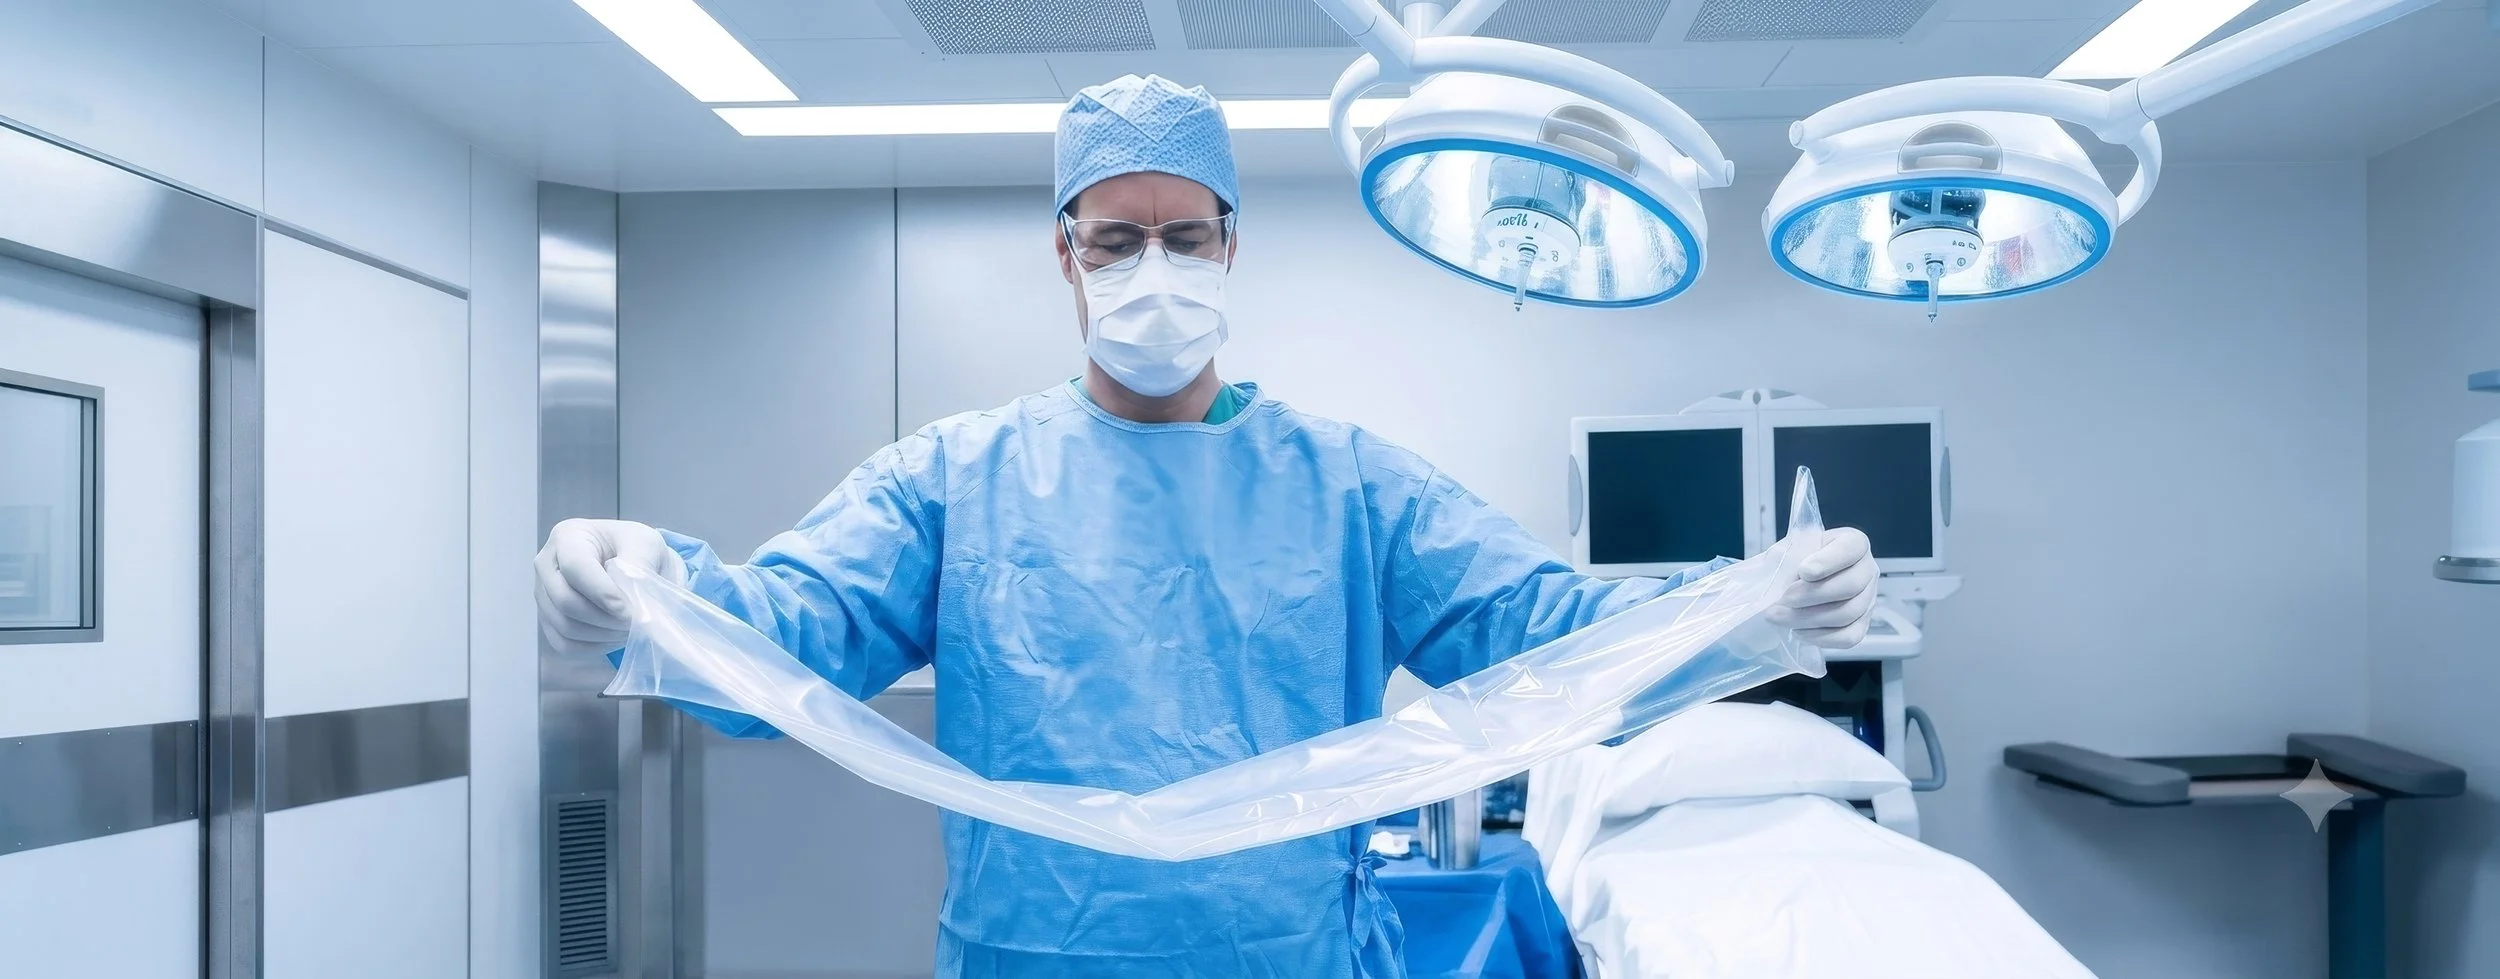
WEG Surgical Solutions Warming and Slush Systems are designed with expert nurses to reduce unexpected events during surgical procedures. The systems are built to precisely control temperature, aid drape placement and provide additional protection to help prevent breach of the sterile barrier. We therefore only recommend the use of WEG Drapes with the WEG Warmers and WEG Slush.
-
You can learn about the drapes and the warmer system on our WEG Warmer page, but here is a quick rundown:
The warmer drapes have embedded frames that are designed to fit the basins and allows easy and exact placement every time.
The Warmer drapes are dual layer with a low friction layer that allows easy placement and a high friction layer provides stability.
Dual layer drapes provide added protection for the sterile barrier.
The WEG Slush drapes are designed to snap into place and stay in place the entire procedure.
Slush drapes are designed to also fit into legacy slush machines allowing the WEG Slush drape to be used on ALL of your slush machines.
-
At power up, the temperature is set to 104ºF which is in line with the AORN guidelines for irrigation fluids.
After start-up, the temperature can be manually adjusted, either up or down from the pre-set temperature of 104ºF Temperature adjustment directions are located on the WEG Warmer next to the controller.
The Warmer will always start up at the pre-set 104ºF temperature, NOT the last temperature adjustment.
-
No, the WEG Slush machine is equipped with our automatic,dual-mode intelligent cooling. The start mode delivers a rapid initial rate of cooling for quick slush production and then automatically switches into the maintenance mode to maintain optimal slush consistency throughout the entire procedure, no matter how long it lasts
-
Starting with 2 liters of room temperature sterile saline, you can expect to have smooth, fully formed slush in 25-30 minutes. Starting with pre-chilled saline, you can reduce your time to fully formed slush to 20-25 minutes.
WEG Customer Support
References
1. Knaepel A. Inadvertent perioperative hypothermia: a literature review. J Perioper Pract. 2012;22(3):86-90. 2. Burger L, Fitzpatrick J 2009 Prevention of inadvertent perioperative hypothermia British Journal of Nursing 18 (8): 1114 - 11193. Lynch S, Dixon J, Leary D 2010 Reducing the risk of unplanned perioperative hypothermia AORN Journal 92 (5): 553 - 65 4. Craft TM, Upton PM (2001) Key Topics in Anaesthesia: Clinical Aspects. BIOS Scientific Publishers, Oxford 5. Jeran L (2001) Patient temperature: an introduction to the clinical guideline for the prevention of unplanned perioperative hypothermia. J Perianesth Nurs 16(5): 303–13 6. Bernthal EMM (1999) Inadvertent hypothermia prevention: the anaesthetic nurses` role. Br J Nurs 8(1): 17–25 7. Fiedler MA (2001) Thermoregulation: anaesthetic and perioperative concerns. J Am Assoc Nurse Anesth 69(6): 485–91. 8. Lawing C, Hedrick L, Startzman A. How to Manage Intraoperative Contamination. Journal of the Pediatric Orthopaedic Society of North America. 2026;14:100298. doi:10.1016/j.jposna.2025.100298